
Medically reviewed by
USA Pain Center Medical Review Team
Interventional radiologists focused on knee arthritis
Date: August 2026
The number one mistake that makes knee pain worse is ignoring it. When discomfort develops gradually, many people assume it will resolve on its own. They push through their daily routine, delay evaluation, and avoid conversations with a specialist. Over time, this approach allows the underlying cause — most often inflammation tied to knee osteoarthritis — to progress unchecked.
But ignoring pain is not the only mistake that makes knee problems worse. There is an equally common error on the opposite end: going completely inactive when pain strikes. Complete rest weakens the muscles that support the knee, reduces circulation to the joint, and can accelerate stiffness. Neither extreme — pushing through pain nor avoiding all movement — serves your joint health.
What most patients don’t realize is that knee pain, particularly the chronic kind, is frequently driven by a biological process: abnormal blood vessel growth inside the knee joint that fuels ongoing knee inflammation. This is not simply a matter of wear and tear. The joint’s inflammatory response can intensify regardless of whether you are resting or staying active — which is why addressing the root cause matters more than adjusting activity alone.
This guide covers the most common mistakes that make knee pain worse, how treatment options compare, how to find smarter relief at home, which symptoms signal something serious, and when it is time to speak with a knee pain specialist.
The Number One Mistake: Ignoring Knee Pain
Knee pain is your body’s warning signal. When it appears after climbing stairs, after a long walk, or first thing in the morning, it is telling you that something in the joint needs attention. Pushing through that signal — continuing high-impact activities without addressing the cause — is the most common and consequential mistake patients make.
Untreated knee pain, particularly when it stems from knee osteoarthritis, tends to progress rather than resolve. Cartilage does not regenerate on its own. Inflammation, once established in the joint, can become a self-sustaining process. Abnormal blood vessels grow into the joint lining (the synovium), carrying inflammatory signals and nerve fibers that intensify pain over time.[1] Without intervention, this cycle may continue regardless of your activity level.
Early evaluation can help identify the source of your pain before joint damage progresses. The early signs of knee arthritis are often subtle — recognizing them sooner means more options tend to be available.
The Other Mistake: Going Completely Inactive
Many people swing to the opposite extreme when knee pain develops: they stop moving almost entirely. This approach, while understandable, can backfire.
Movement keeps blood flowing to joint tissue, helps cartilage receive nutrients, and maintains the muscle strength that offloads pressure from the knee itself.[2] When the quadriceps and surrounding muscles weaken from disuse, the joint absorbs more stress with every step.
For people living with knee osteoarthritis, balancing appropriate activity with symptom management can help maintain mobility while also recognizing when additional treatment may be needed.
Low-impact movement — like walking on flat surfaces, swimming, or seated stretching — can help maintain mobility without placing excessive load on an inflamed joint. A 2025 network meta-analysis of 139 clinical trials found that exercise-based therapies remain among the most effective non-drug approaches for knee arthritis pain and function.[3] The goal is controlled, appropriate activity — not rest and not strain.
Other Common Habits That Make Knee Pain Worse
Beyond ignoring pain or going fully inactive, several additional behaviors can accelerate joint damage or delay recovery:
Continuing High-Impact Activities
Running, jumping, and repetitive squatting on an already inflamed knee adds stress to cartilage and joint tissue. High-impact activity is not appropriate when the joint is actively inflamed or symptomatic.
Relying Only on Pain Medication
Over-the-counter pain relievers can make movement feel more manageable, but they do not address the source of knee pain. Masking pain without treating the cause may allow the underlying condition to advance. Patients may also continue activities that worsen joint health because the pain signal has been reduced.
Waiting Too Long to Seek Care
Many adults live with knee pain for months or even years before consulting a specialist. By the time they do, the condition may be more advanced and harder to manage conservatively. This delay is especially common among adults over 60, who may attribute knee pain to normal aging.
Poor Footwear Choices
Shoes without adequate support alter your body’s alignment and shift load onto the knees. Footwear that is worn down, flat, or unsupportive can quietly contribute to worsening joint stress over time.
How Treatment Options Compare: From Conservative Care to GAE
Understanding how different approaches work — and where each fits — can help you and your specialist find the right path forward. Knee osteoarthritis treatment typically follows a stepwise progression from lifestyle changes to more targeted interventions.
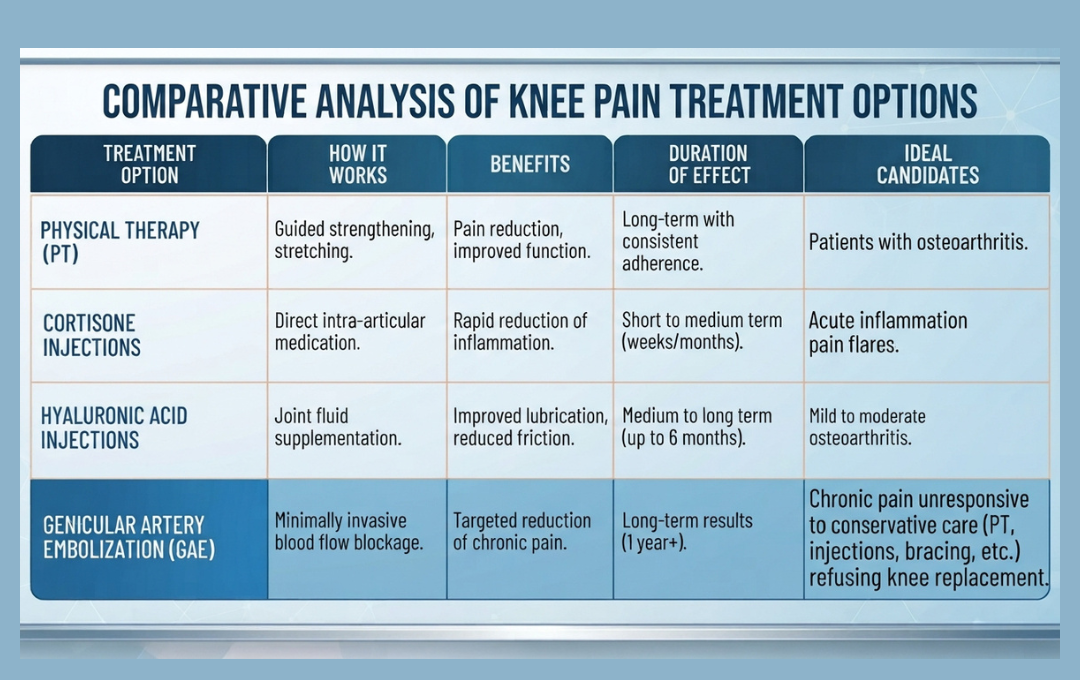
Physical Therapy and Exercise
Physical therapy is one of the most consistently recommended first-line treatments for knee osteoarthritis. Strengthening the quadriceps and surrounding muscles reduces the load the knee joint must absorb with each step. A large 2025 meta-analysis found that exercise-based therapy produces clinically meaningful improvements in pain and function.[3] These gains require consistent effort over time and work best earlier in the disease course.
Cortisone (Corticosteroid) Injections
Cortisone shots reduce joint inflammation quickly — most patients feel relief within 24 to 72 hours. The benefit typically lasts six to twelve weeks. The trade-off is that they are a short-term measure, not a long-term solution. A 2025 study confirmed that repeated cortisone injections are associated with greater progression of knee osteoarthritis on imaging.[4] Most guidelines recommend no more than three to four injections per year, with at least three months between treatments.
Hyaluronic Acid (Gel) Injections
Hyaluronic acid injections add lubrication to the joint and may reduce friction and pain. Relief tends to last longer than cortisone — often three to six months, and sometimes beyond one year with repeated courses. These injections do not address the inflammatory process directly and work best in mild to moderate osteoarthritis.
Genicular Artery Embolization (GAE)
Genicular artery embolization (GAE) is a minimally invasive, outpatient procedure performed by an interventional radiologist. Using image guidance, a thin catheter is positioned near the genicular arteries — the small blood vessels supplying the inflamed knee lining. Microscopic particles are delivered to reduce abnormal blood flow in those vessels, targeting the hypervascularity that sustains joint inflammation.[5]
Clinical evidence from the past two years continues to support GAE for appropriate candidates. A 2025 UCLA analysis of 236 patients found durable improvement at one year, with the strongest outcomes in younger patients and those with earlier-stage osteoarthritis.[6] A 2024 prospective trial with two-year follow-up found that 72% of patients who responded at 12 months maintained that improvement at 24 months.[7] A 2026 randomized study comparing GAE to standard care reported a 72.7% improvement in pain scores in the GAE arm versus 24.2% in the control group at one year.[8]
GAE is best suited for patients with osteoarthritis-related knee pain who have not found lasting relief from conservative care and are not candidates for, or do not desire, joint replacement. A candidacy evaluation with a specialist is needed to determine if GAE is appropriate.
What Is the Most Common Cause of Knee Pain in Seniors?
Knee osteoarthritis is the leading cause of chronic knee pain in older adults. It occurs when the cartilage cushioning the knee joint gradually breaks down, eventually leading to bone-on-bone friction, inflammation, and stiffness.[9] In adults over 60, osteoarthritis accounts for the majority of persistent knee pain cases.
Recognizing the early signs of knee arthritis — morning stiffness that takes more than 30 minutes to resolve, pain that worsens with activity and improves with rest, or a grinding sensation during movement — can help older adults seek timely evaluation before the condition progresses to more advanced stages.
What Is the Fastest Way to Relieve Knee Pain at Home?
When knee pain flares, several home approaches may help reduce discomfort in the short term:
Rest the Joint Temporarily
Reduce or pause the activity that triggered pain, but avoid prolonged inactivity. A brief rest period followed by gentle movement is generally more helpful than complete bed rest.
Apply Ice
Applying an ice pack wrapped in a cloth for 15 to 20 minutes may help reduce acute swelling and discomfort. This is most effective in the first 24 to 48 hours after a flare.
Elevate the Leg
Keeping the leg elevated while resting can help reduce fluid buildup in the joint.
Use a Supportive Brace
A soft knee brace or compression sleeve may help stabilize the joint during activity and reduce pain perception during movement.
Gentle Range-of-Motion Exercises
Seated knee bends, heel slides, and straight-leg raises can help maintain mobility without loading the joint. These approaches can help manage acute pain, but they are not a substitute for evaluation if knee pain persists, worsens, or comes with swelling, instability, or limited range of motion.
What Are Red Flags in Knee Pain?
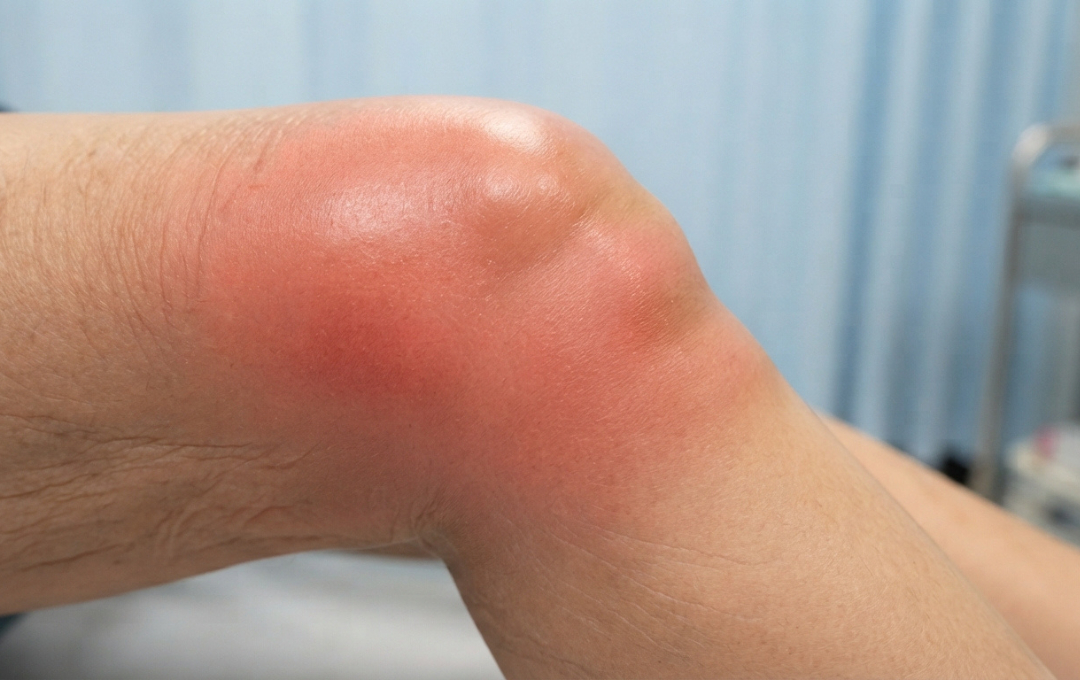
Most knee pain is manageable and responds to conservative care over time. However, certain symptoms signal that the joint needs prompt professional evaluation:
Sudden, Severe Swelling
Rapid swelling of the knee, particularly after a minor incident, may indicate a fracture, ligament tear, or significant internal injury.
Inability to Bear Weight
If putting weight on the knee causes intense pain or feels impossible, this requires same-day or urgent evaluation.
Knee Locking
A sensation that the knee is stuck or locked in one position — especially if it cannot be straightened — may indicate a loose body or structural issue inside the joint.
Redness, Warmth, and Fever
These signs together may indicate a joint infection (septic arthritis), which is a medical emergency.
Significant Instability or Buckling
If the knee repeatedly gives way during routine activities like standing or walking, structural damage may be present.
Pain That Does Not Improve Within Six Weeks
Persistent knee pain that does not respond to rest, activity modification, or over-the-counter care warrants specialist evaluation.[10]
When to Speak with a Knee Pain Specialist
If knee pain is affecting your daily activities, has lasted more than a few weeks, or comes with any of the red flags above, consulting a specialist is the appropriate next step. Early evaluation helps identify the root cause — whether that is osteoarthritis, inflammation, or a structural concern — and opens the door to targeted treatment options.
For patients with chronic knee pain tied to inflammation from osteoarthritis, minimally invasive options like genicular artery embolization (GAE) may reduce pain by targeting the abnormal blood flow that sustains joint inflammation. GAE is an outpatient procedure using image-guided techniques and does not require open-joint access. A specialist evaluation determines candidacy.
Treatment option: minimally invasive care
When Knee Pain Needs More Than Home Care
Conservative steps like rest, ice, and activity modification can help in the short term, but they don’t address the source of chronic knee inflammation. When pain persists despite lifestyle changes, a specialist evaluation is the clearest path forward.
USA Pain Center uses advanced imaging and minimally invasive techniques to assess and treat chronic knee pain tied to osteoarthritis. If you’re ready to understand what’s driving your pain, a consultation is a good place to start.
Frequently Asked Questions About Knee Pain
- Hunter DJ, Bierma-Zeinstra S. Osteoarthritis. The Lancet. 2019;393(10182):1745-1759.
- Cleveland Clinic. Osteoarthritis of the Knee. Cleveland Clinic Health Library. 2024.
- Physical Medicine and Rehabilitation Clinics of North America. Network meta-analysis of exercise therapies for knee osteoarthritis. 2026;37(3):395-405.
- Radiological Society of North America. Repeated corticosteroid injections and knee OA progression on imaging. 2025.
- Ahmed O, Sajan A, Krishnasamy V, et al. Genicular Artery Embolization for Symptomatic Knee Osteoarthritis: A Comprehensive Review. Cardiovasc Intervent Radiol. 2025;48:1737-1754.
- Callese T, Cusumano L, Sparks H, et al. Early intervention in knee osteoarthritis with genicular artery embolization. European Radiology. 2025 Dec;35(12):7617-7626.
- Genicular Artery Embolization for Treatment of Symptomatic Knee Osteoarthritis: 2-Year Outcomes from a Prospective IDE Trial. J Vasc Interv Radiol. 2024.
- Genicular artery embolisation in patients with symptomatic knee osteoarthritis: Prospective randomised study. ScienceDirect. 2026.
- National Institute of Arthritis and Musculoskeletal and Skin Diseases. Osteoarthritis. NIH/NIAMS. 2024.
- Bijlsma JW, Berenbaum F, Lafeber FP. Osteoarthritis: an update with relevance for clinical practice. The Lancet. 2011;377(9783):2115-2126.
Medical disclaimer: USA Pain Center content provides medical education only. It is not a diagnosis or treatment recommendation. Consult a pain management specialist for evaluation.
